Wedge, Sill or Both? Why Alarplasty Results Vary So Much Between Patients
Two people can walk into a consultation saying the same thing — my nostrils are too wide — and leave with two different operations planned. Not because one surgeon disagreed with another, but because the phrase ‘wide nostrils’ describes at least three different anatomical situations, and each one responds to a different excision.
Understanding which situation applies to you is most of the decision. The technique name is almost an afterthought.
First, a terminology correction
Direct answer: wedge, sill and Weir are not three separate competing techniques. Weir is a historical eponym — Robert Weir described alar base excision in 1892 — and in modern usage ‘Weir excision’ generally functions as an umbrella term for alar base reduction. Wedge and sill excisions are specific patterns within that category, and they are frequently combined.
This matters because a good deal of what is written online treats them as three options on a menu, which leads patients to ask ‘which is best?’ — a question with no answer. The useful question is what tissue needs removing, and from where.
The three anatomical situations
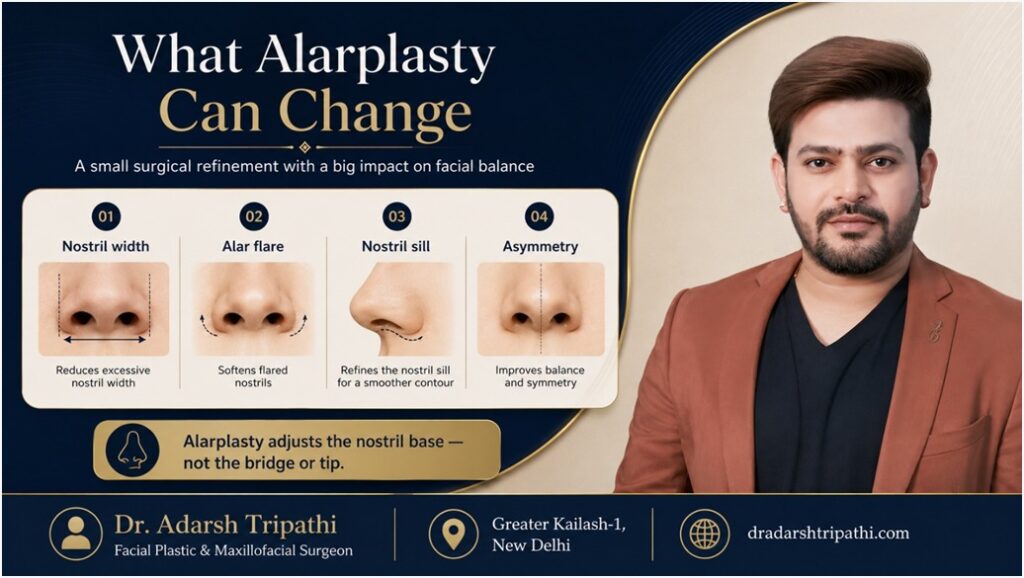
Alar flare — the nostrils spread outward
Here the width is in the outer wall of the nostril. Viewed from the front, the alae extend beyond the width of the nasal base and often beyond a line dropped from the inner corner of each eye. From below, the nostril openings themselves may be a reasonable size — the problem is the outward curve of the wall around them.
This is what wedge excision addresses. A wedge of tissue is removed from the outer ala, the edges are brought together, and the flare reduces. The nostril opening itself changes relatively little.
Wide nostril floor — the base itself is broad
Here the distance between the two nostril openings across the base of the nose is the issue. The alae may not flare outward at all. Viewed from below, the nostrils sit far apart and the sill — the floor of the nostril where it meets the upper lip — is wide.
Wedge excision does not fix this. Removing tissue from the outer wall narrows the outside of the nose while leaving the floor as wide as it was. Sill excision removes tissue from the nostril floor itself, which brings the base inward.
Both together
Many patients have some of each, which is why combined excisions are common. The judgement is not which technique but how much from each location, and in what proportion.
What each excision changes — and what it does not
| Anatomical concern | Excision considered | What it changes | Important limitation |
| Outward alar flare | Alar wedge | Reduces the outward projection of the nostril wall on frontal view | Does little for base width across the floor. Over-resection risks alar notching |
| Wide nostril floor / base | Sill excision | Brings the nostril base inward, narrowing the distance across the floor | Does not reduce outward flare. Excessive removal can narrow the airway |
| Both flare and base width | Combined | Addresses both dimensions | More tissue handled means more scope for asymmetry — requires careful measurement |
| Width from poor tip projection | Often neither alone | — | Base reduction may narrow the nose while leaving it looking unbalanced. Tip work may be needed |
| Asymmetric nostrils | Asymmetric excision | Can improve balance | Asymmetry is normal. Perfect matching is not a realistic goal |
Note: This table is a framework for understanding the conversation, not a way to self-diagnose. Which situation applies to you is established by examination, particularly from the basal view.
Why two patients with ‘wide nostrils’ may need different operations
This is where the reasoning becomes concrete. Consider two people who describe their concern identically.
Patient A: from the front, the nostrils extend well beyond the nasal base. From below, the nostril openings are ordinary in size and the floor is not especially wide. The tip projects normally. This is flare. A wedge excision addresses it directly, and a sill excision would narrow an airway that did not need narrowing.
Patient B: from the front, the nose looks wide but the alae do not obviously curve outward. From below, the nostrils sit far apart with a broad floor. Here a wedge excision would remove tissue from a wall that was not the problem — narrowing the outside slightly while the base stays wide. Sill excision is the more logical approach.
And a third case worth knowing about: a patient whose nose looks wide at the base largely because the tip lacks projection. Reducing the alar base in isolation can produce a nose that is narrower and still looks unbalanced — sometimes more so, because the tip now appears flatter against a narrower base. This is one of the more common reasons a surgeon might recommend addressing the base as part of a rhinoplasty rather than alone.
Why one extra millimetre matters
Direct answer: because the alar base is small, and the change is proportionally large. A millimetre removed from each side is two millimetres off a structure that may only be twenty-five to thirty millimetres across at the relevant point. Proportionally, that is a substantial change — and it cannot be reversed.
This asymmetry between over- and under-correction shapes how careful surgeons plan. Taking slightly too little leaves an easily solved problem: a small second excision once healing is complete. Taking slightly too much leaves alar notching, a pinched look in animation, or an airway that feels tighter — none of which has a straightforward fix, because the tissue is gone.
If your surgeon proposes taking less than you were expecting, that is usually experience talking.
Why the technique name matters less than the diagnosis
Patients often arrive having decided they want a particular technique, usually because they read that it produces better scars or more natural results. Neither claim survives contact with the anatomy.
A wedge excision performed on a patient whose problem is base width will produce a disappointing result no matter how well it is executed. A sill excision on a patient whose problem is flare will do the same. The technique is downstream of the diagnosis, and the diagnosis requires looking at the nose from below, at rest and in animation, and in the context of the rest of the face.
Which is the real answer to the question this article opened with. Results vary between patients not mainly because surgeons differ in skill — though they do — but because the operation was matched, or not matched, to the anatomy.Covers how to assess whether a surgeon is making that judgement properly.
What about scars?
Alar base incisions sit in or very close to the natural crease where the nostril meets the cheek, which is why they usually heal inconspicuously. Sill incisions sit at the nostril floor and are hidden by the position of the nose itself.
Scar quality depends on incision placement, tension across the closure, skin type and individual healing tendency. Mature scarring takes several months. Nobody can promise an invisible scar, and claims to the contrary are worth treating cautiously — but in most patients these are among the better-hidden facial incisions.
If nostril width is your concern
The single most useful thing an assessment establishes is whether your width is flare, floor, or structural — because that decides everything that follows. Our alarplasty treatment page sets out the procedure, recovery and costs. Dr. Adarsh Tripathi is a maxillofacial and facial plastic surgeon at Sarayu Clinics, Greater Kailash-1, and also performs rhinoplasty — which matters here, because it means the recommendation is not limited to what a base reduction alone can achieve.
FAQS
What is the difference between wedge and sill alarplasty?
A wedge excision removes tissue from the outer wall of the nostril to reduce outward flare. A sill excision removes tissue from the nostril floor to narrow the distance across the base. They address different dimensions of width, and many patients need a combination of both.
What is a Weir excision?
Weir is a historical name — Robert Weir described alar base excision in 1892 — and it is generally used today as an umbrella term for alar base reduction rather than a distinct third technique. Wedge and sill excisions are specific patterns within it. Sources treating Weir as a separate competing option are using the term loosely.
Which alarplasty technique gives the best result?
There is no single best technique. The right approach depends on whether the main problem is outward alar flare, excessive nostril floor width, overall base width, asymmetry, or a combination. A technique matched to the wrong anatomy produces a poor result however well it is performed.
Can alarplasty affect my breathing?
Excessive sill excision can narrow the nostril opening enough to affect airflow, which is one reason conservative removal matters. Appropriately planned alarplasty should not compromise breathing. If you already have a breathing problem, that should be assessed separately — it is usually a structural issue inside the nose rather than at the base.
Will alarplasty alone make my nose look narrower?
It depends where your width comes from. If the width is genuinely at the alar base, yes. If the nose looks wide partly because the tip lacks projection, reducing the base alone may narrow the nose while leaving it looking unbalanced. This is established at examination.
How much tissue is usually removed?
Typically a few millimetres per side, and the exact amount is planned individually from measurements taken during examination. Because the alar base is a small structure, small differences produce visible changes — which is why experienced surgeons tend toward conservative removal.